
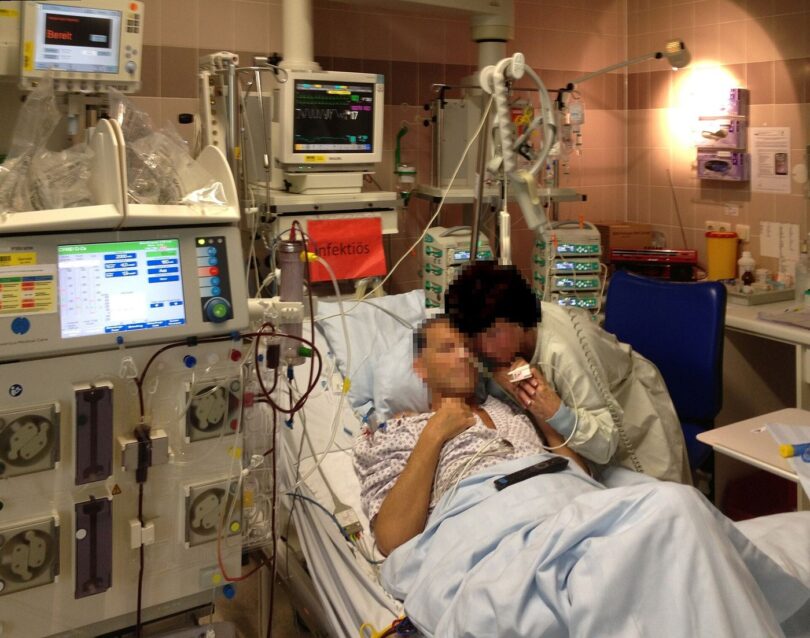

Sepsis is one of the deadliest conditions in medicine, yet many people have never heard of it. It begins with an infection, often pneumonia, a urinary infection or a wound, and turns dangerous when the body’s own immune response spirals out of control and starts damaging its organs. The heart, lungs, kidneys and brain can fail in hours, and without rapid treatment the condition is often fatal. The Global Burden of Disease study estimated 48.9 million cases and 11 million deaths from sepsis worldwide in 2017, nearly one in five of all deaths on the planet, with children under five accounting for around half of the cases. The numbers are far higher than earlier estimates, which were based only on hospital records from a handful of wealthy countries. Sepsis kills more people than many cancers, yet it receives a fraction of the attention.
What the Evidence Shows
The tragedy is that much of it is preventable and much of it is treatable if caught early. Vaccination, clean water, hand hygiene and prompt treatment of infections all reduce the risk, and the World Health Organization has called sepsis a global health priority since 2017. In hospitals, the key is speed: recognising the warning signs, such as confusion, rapid breathing, low blood pressure and mottled skin, and starting antibiotics and fluids within the first hour. Campaigns in several countries now teach the public to ask “could this be sepsis?” when an infection suddenly worsens. Survival also depends on where a patient lives: death rates are far higher in low-income countries, where intensive care is scarce. Early recognition remains the single most powerful treatment we have. Teaching families and carers to spot the warning signs may matter as much as any drug in the hospital pharmacy. Reporting and analysis from sources such as National Science Foundation track the same developments, and specialists following sepsis recognition say the direction is now consistent across independent lines of evidence.
The Wider Context
The wider context is a research landscape in which replication and open data now decide reputations. Findings connected to sepsis recognition are being checked by independent groups with shared datasets, and the teams involved publish their methods in full so rivals can test every step. That discipline is slower than a headline cycle, but it is why results in this area increasingly survive first contact with scrutiny.
What Happens Next
What happens next in the story of sepsis recognition will be decided by follow-up work already under way: larger samples, longer observation and instruments that have not yet come online. The researchers involved are unusually united on one point, that the current results justify the next investment of time and money. Readers will not have to wait long for the first tests of that claim. You can follow related developments in our coverage of science.
There is a practical lesson in all of this for readers deciding what to do today. Start with the verified facts, be wary of anyone promising certainty, and prefer reversible steps while the evidence is still developing. Circumstances differ by country, income and personal situation, so general guidance should always be weighed against your own context before you act on it in any significant or lasting way.






